

Here’s a well thought out Tweet on Healthcare.
That chart is a disaster. It’s from the New York Times article below.
First, let’s discuss a shortage of nurses and doctors.
Healthcare Crisis (Above Tweet)
America already has serious shortages of doctors and nurses. Yet republicans are making it harder to keep the healthcare workers we already have.
About 56,000 nurses working in the U.S. in 2023 came from countries now subject to complete immigration bans. Nearly 24,000 physicians did too.
And these aren’t abstract numbers.
Maureen Ngure, a nurse who had lived in the U.S. since 2006 and worked on the COVID front lines, was detained by ICE and deported to Kenya.
Debora Kapisha, a registered nurse at Maine Medical Center who was authorized to work in the U.S. through 2030, was detained by ICE.
Monica Ryadi, a registered nurse who has lived in the U.S. since she was a child, was detained at LAX while taking her family to Disneyland. She spent two weeks in ICE detention.
And physicians aren’t immune either:
Dr. Rubilez Bolivar, an emergency medicine resident with a valid work permit, was detained while traveling with her 5-year-old U.S.-citizen daughter to a scheduled asylum interview.
Dr. Ezequiel Veliz, a family physician serving the Rio Grande Valley, was detained at a Border Patrol checkpoint.
These are nurses and doctors who were already here. Already working. Legally. Already taking care of American patients.
You can’t make healthcare more affordable by making it harder to get healthcare.
Thank You Dittie.
Employer Health Costs Are Expected to Spike in 2027
The New York Times reports Employer Health Costs Are Expected to Spike in 2027
A new U.S. survey anticipates an average increase of 11 percent unless benefits are cut, the highest rate in decades. Other findings also predict a sharp rise.
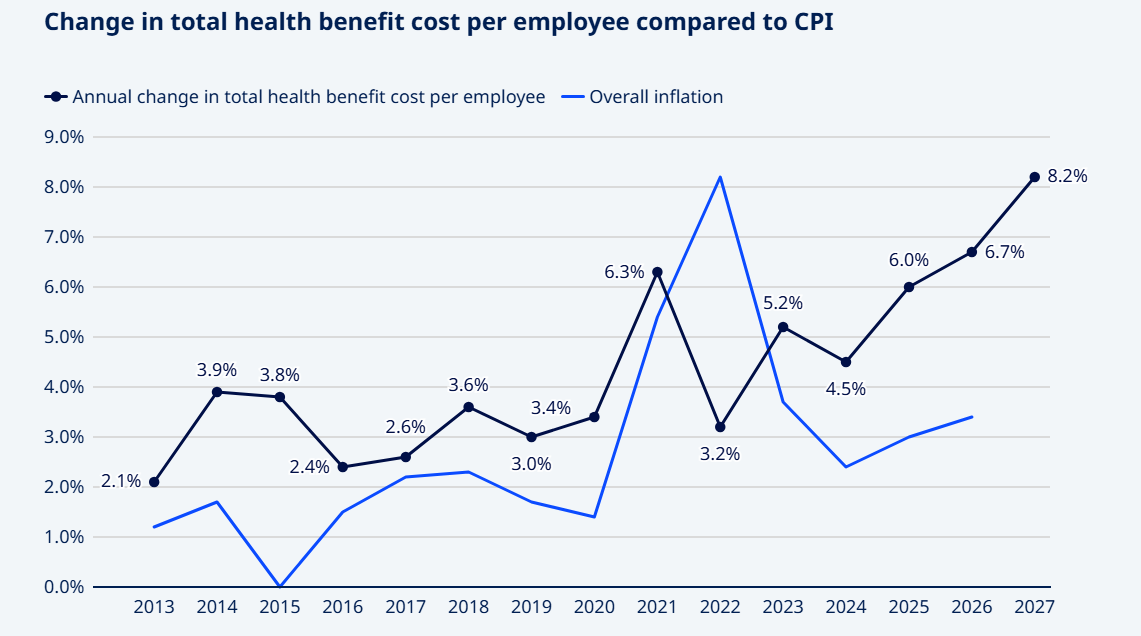
Large and small employers are bracing for what looks to be the sharpest increase in health care costs in more than two decades. The cost per worker is projected to go up an average of 11 percent next year, or somewhat lower if workers’ insurance benefits are reduced.
The employers’ final costs, after they make changes to health plans, are still expected to increase about 8 percent next year, the steepest since 2003, according to Marsh, the benefits consultant formerly known as Mercer.
More than a third of the 1,800 employers surveyed said they anticipated that costs would rise at least 10 percent after making cuts.
“This seems to be a new normal,” said Ellen Kelsay, the chief executive of Business Group on Health, which represents large employers that offer health benefits.
From 2018 to 2027, health care costs could increase 76 percent, roughly twice the rate of general inflation, according to a survey the employer group released last month. For next year, companies predicted a 9.2 percent median increase, which fell to 8 percent after they made benefit changes.
The cost of providing coverage to employees is becoming an existential business issue, said Mike Pasterick, an executive at the insurance broker Aon, which issued its own projection last month. Aon estimated employers’ costs would rise 9.5 percent next year, pushing the average cost per employee above $19,000 if no changes are made. “This is impacting the companies in a very material way,” he said.
The upshot is that about 160 million people under 65 who rely on employers for health insurance will again confront higher costs and shoulder more of the burden. More and more, workers are facing year-over-year increases that further stress household budgets already dealing with the growing expenses of groceries and gasoline.
Workers are facing higher premiums, deductibles and co-pays, which require them to carry a larger share of their medical bills. Some companies are cutting benefits by discontinuing coverage of expensive GLP-1 drugs to treat obesity, or dropping coverage for spouses who have other insurance options.
Trump’s Laughable Answer
When Idaho Banned Abortion
Please consider When Idaho Banned Abortion, OB-GYNs Fled. The Doctors Who Stayed Are Cracking.
In the four years since the U.S. Supreme Court overturned Roe v. Wade, triggering a near-total ban on abortion in Idaho, with the potential for criminal prosecution of any doctor who performed the procedure, OB-GYNs have been fleeing the state in extraordinary numbers. More than a third of Idaho’s OB-GYNs have stopped practicing obstetrics, left the state, closed their practices or retired since the ban took effect in August 2022, according to a study published in The Journal of the American Medical Association last year. By December 2025, there were just 170 obstetricians for the state’s roughly one million women — fewer than two doctors per 10,000. About five full-time maternal-fetal-medicine specialists, who serve the riskiest pregnancies, remained, according to a separate report released in 2024. One half of Idaho’s 44 counties no longer have a practicing obstetrician.
The impact of the exodus has rippled across the state. Since 2023, three hospitals in rural parts of Idaho have shuttered their labor and delivery wards because of staffing shortages. In the southeastern corner of the state, one OB-GYN serves a population of more than 120,000 people, according to a recent paper by a researcher at Oregon State University. Even in more populated areas, like Boise, OB-GYNs are so overloaded that the wait for a hysterectomy can be six months. It can take nine months to secure an appointment for an annual exam. Increasingly, hospital administrators say, women facing life-threatening complications are loaded into a helicopter and flown out of state for treatment that OB-GYNs in Idaho are not allowed to administer.
Idaho voters reject ballot measure on abortion
Please note Idaho voters reject ballot measure on abortion, preserving the state’s ban, NBC News projects
The Reproductive Freedom and Privacy Act Initiative, also known as Proposition 1, would have gone into effect in 2027. Proposition 1 would have allowed the government to regulate abortion only after fetal viability, except in the case of a medical emergency to save the life of the woman.
The initiative said Idahoans have a right to make their own decisions about abortion, childbirth care, contraception, fertility treatment, miscarriage care and prenatal, pregnancy and postpartum care.
According to the Center for Reproductive Rights website, from 2022 to earlier this year, 11 states expanded access to abortion and reproductive care since the Supreme Court’s Dobbs decision.
Almost a third of Idaho’s OB-GYNs moved away, stopped practicing or retired from August 2022 to December 2024, according to a study published in a medical journal.
Affordable Care Act Rates to Rise Steeply Again
The Wall Street Journal reports Affordable Care Act Rates to Rise Steeply Again
Quick Summary
- Affordable Care Act plan premiums will rise by 13% in 2027, marking the second straight year of double-digit increases, according to KFF.
- The premium hike is driven by growth in spending in areas like hospital care and drugs.
- Cigna Group is pulling out of the ACA market entirely next year, amid 31 state-level departures by insurers.
Change is coming. The election results guarantee that.
Related Posts
November 5, 2026: Democrats Take Over 250 House Seats in Huge Power Shift
The counting is still not over. I am eyeing 262 minimum.
And In case you missed it, please see Trump’s Legacy and a Word of Thanks to MishTalk Readers
My reflections on one of the biggest political wipeouts in history, plus a word of thanks.


This is what the health expert from Taiwan said in an interview explaining why they went for a universal Medicare-type system : “Well, American is not really a system that you can copy. It’s a market. So if you let things happen, it will be like the United States. There [were] many supporters [in Taiwan], but in the end we said, ‘No, this is not the way we want to go.’ “
Turns out we do need Medicare for all. Take it out of the DOD and CIA funds.
We will need at least another election like the last one, removing the corrupt sociopaths that are in congress now and owned by corporations and Israel.
1. Healthcare is not a market good. In order to have a “market”, one needs an de facto infinite number of buyers and sellers, price transparency, and no information asymmetries. Healthcare offers none of these things, except perhaps an infinite number of buyers.
Unless you have medical training or otherwise have a fair amount of smarts and a *lot* of time on your hands, neither you or I have any idea whether a recommended course of treatment is:
*medically necessary
*not the standard course of treatment but supported by an educated minority of informed medical opinion
*generally safe and effective but cheaper options are available
*pure quackery
*contraindicated in your particular case
*an appropriate treatment but you can get something similar for less at the other clinic down the street
*an appropriate course of treatment but another provider can perform it better
*palliative at most
*superseded by new methods of treatment
*something else
*more than one of the above
Now, imagine that you are lying flat on your back in the ER in Stutsman County, North Dakota. Are you going to look over a menu of treatment options and bargain and discuss qualifications with that nice Dr. Finster, washing between his toes in the corner over there? Or are you going to take your chances and hope that you don’t bleed out before you can Uber it over to the next nearest ER, which is only 40 miles away?
Then throw in health insurance. That means that we are mostly spending other people’s money. At the same time, medical procedures are expensive enough that for most of us, paying out of pocket is not really an option.
2. Anyone with as brains as God gave a baby rabbit can tell that the US healthcare system is utterly dysfunctional. By any objective measure, it delivers substandard outcomes and does so at exorbitant cost.
The problem is that all those inefficiencies mean profits. (Market theoreticians say that in a perfect market, everyone breaks even, which in turn demonstrates just how imperfect the US healthcare market is, but that is another matter.)
Everyone agrees that reform is needed and inefficiencies eliminated. The problem is that the there are a lot of people and institutions that profit off those inefficiencies. None of them want their slice of the pie to be touched, all of them are entrenched and all of them have their congressmen on speed dial.
To give a few examples:
*The AMA
*The trial lawyers
*The HMOs and hospitals
*The insurance companies
*The alternative medicine industry (because legit medical care is expensive)
*The pharma manufacturers (generic and name brand have somewhat different interests at stake here)
*The unions (many of which run their own health insurance plans)
Any real reform will put some of the above out of business, and will substantially limit the profits available to others.
For instance, can you imagine the howling from the AMA if reforms had the effect of reducing doctors’ salaries to European levels? “How am I supposed to keep two ex-wives and a Porsche on a measly $85K a year?” For that matter, the ex-wives and the Porsche dealer won’t be too happy, either.
These interests don’t necessarily line up with one political party or the other, so it’s not like we can just vote Team D or Team R and we got the problem licked. The people in charge of these interests have careers and vacation homes at stake, and they are going to fight against reform a lot harder than someone not invested in the status quo will fight for reform.
3. I have often heard it said that state run healthcare will kill entrepreneurship. Quite the opposite. A lot of people would love to set up on their own, but health insurance costs make it impossible. That goes double if you have a kitten with a pre-existing condition.
Well said Feral
As of 2025, 12% of the national workforce is employed in the Healthcare industry…19-20 million people. These folks may not want the same reform you (and I) are advocating for!
The one thing that will make it more affordable is doing what any of the other OECD nations with universal health care have done.
This is not rocket science. Many countries have developed systems that address this issue. To be sure, no system is perfect. But that doesn’t mean there is just no other direction in which our system can evolve.
Single payers can dictate compensation for medical services and control drug and test prices. Those fat cat doctors won’t make 700k/year and will be very unhappy. I know most front-line doctors don’t make 700k but salary controls will result in shortages of all medical personnel. I understand France has a serious nurse shortage.
I’m 81 and exercise, maintain a healthy weight and eat a lot of plants. That’s how I handle the problem, but most Americans are short on self discipline and need a lot of drugs and procedures.
Well, the US has similar shortages too, and on top of it, has much higher turnover volatility.
Entrenched interests will never allow it.
What we call “inefficiencies”, others call “vacation homes”.
There is no market
It’s true in the US, but also in countries with national health service or government mandates [like compulsory private insurance & stipulations about basic coverage]. In countries with private insurance you see that they merge and consolidate, and land up making decisions about healthcare, diagnostics, organization, etc. And hospitals going bankrupt throw up huge (political) problems.
What do you think would happen to the price of hammers if everybody bought hammers using their mandated hardware insurance?
The healthcare industry is a racket, no price discovery, no competition, perverse incentives, massive monopoly power.
The costs have been going up at double the rate of inflation for decades, consuming an ever greater share of national income. The model is broken, and for some reason anti-trust & racketeering prosecutions are considered to be sacrilege.
+1,000
All the rascals want their cut of the pie. Treatments are way too expensive when multi-layers take a piece of the pie. I paid 7000 plus bucks for a bridge, most of that out of pocket. That’s only one example.
Some truth to this, but even if there were a menu of treatments and procedures clearly marked, most humans would have no idea what any of that meant.
Look at how many humans have wacky health beliefs.
The price of hammers: Corporate lobbying needs to become illegal. Nothing draws in sociopaths, like the big money of corporate lobbying. Remove big money, from government, and you have a chance to have an honest system. For a while. The money and power of government will always be attractive to crooks. We need one or two more election cycles, like this. The result must remove the influence of big corporations and Israel. If that does not happen, then the Fourth Turning follows.
Of course it will, just ban health insurance and all our problems are solved.
In New York State, approximately 32% to 33% of the population is enrolled in Medicaid (around 6.38 million to 7.23 million people depending on the recent monthly or annual average), and about 20% of the population is enrolled in Medicare (roughly 3.99 million people. i have not met a person here who does not like the medicaide coverage here. folks like me who are covered by both programs have great benefits if and when needed. i’m healthy as an ox, so don’t require much but basic human doctoring and pharma……..
So you celebrate that more than half the population of NY has their healthcare paid for or heavily subsidized by taxpayers?
OPM.
In New York State, average Medicaid resource spending comes out to $13,001 per enrollee and approximately $4,942 per state resident (as of FY 2024 data).
Key breakdown details include:
• Per Enrollee Cost: Roughly $13,001 per person enrolled in the program, which is about 17.2% higher than the national average.
• Per Resident Cost: Around $4,942 per total state resident, ranking the highest nationally (roughly 77% to 85% above the U.S. average).
• Total Program Spending: A combined federal and state Medicaid budget of about $98.2 billion (and continuing to scale upward toward $113 billion–$134 billion in subsequent fiscal years).
• Primary Cost Drivers: Managed care plans account for about 53.7% of benefit spending, while long-term services and supports (such as nursing homes and home health care) make up roughly 22.7%
MAGA and all levels of care providers or basic services providers, in terms of affordability, are incompatible.
It’s so funny to me. In 21st century the Ds are the party of more freedom. And the Rs are the party of bigger government. In your bedroom, doctors offices and medicine cabinets and retail stores and consumption of smoking products. I find it very funny. The old Repugs I know are so fucking uptight it makes the Taliban look like blood brothers.
It’s time for health care for all Americans, and the 20% that goes to Big InSura to be returned to direct health care for US citizens. It will be messy; but basic health care is a equivalent-public utility and a right like clean water and K1-K12 education. The Rhodes scholar, MD, valedictorian of University of Michigan class of 2007, and newly Michigan elected senator by a 7 % margin against 40 million dollars or more of oppositional zionist AIPAC money has my support as a retired US Navy physician of 28 years and VA physician of 15 years …
Disagree & define “basic” as overly broad.
American Medical Association (AMA): A major physician lobby and professional organization. Historically, the AMA lobbied for policies that capped residency funding and restricted physician supply, though in recent years it has advocated for removing some of those caps. Critics often debate the AMA’s role in influencing medical training limits and scope-of-practice restrictions.
Canada has been a huge beneficiary of Trumps war on health care and immigration. Hundreds of doctors and nurses have been recruited into Canada’s health care system as the problem with working in the US health care system is that you have to live in the US where violence is any everyday fact of life. Life is good if you are a gun shot wound specialist. Otherwise not so much.
from Mish
Going on a 3-day 2-night backpacking trip.
I will not be able to approve anything that gets caught up needing approval. Multiple links are one possible snare.
Coyote Gulch
Grand-Staircase Escalante
Need a break from this.
But I have many posts scheduled. Three Saturday and I think Three Sunday too. So keep checking.
Some really cool ones Including “Texas Goes Purple and What It Means”
Someone please post this message on my Saturday and Sunday articles.
Mish
Shortage of doctors & nurses is artificial.
Shortage of doctors definitely is. Nurses not so much.
Define “artificial”. For me, it means something that is not real – for you it obviously means something else.
American Medical Association (AMA): A major physician lobby and professional organization. Historically, the AMA lobbied for policies that capped residency funding and restricted physician supply, though in recent years it has advocated for removing some of those caps. Critics often debate the AMA’s role in influencing medical training limits and scope-of-practice restrictions
AMA for sure created the shortage and high salaries. med school just ain’t that hard. probably 10x or more could easily qualify every year to be an MD. of course salaries would be like MD in europe or canada or japan……..it’s a statist guild.
Since during the Clinton battles for Universal Healthcare I’ve been saying:
Are we going tell people to just die when doing so on a hospital doorstep. No (unless it’s asking Stephen Miller when he’s out after dark). Society’s around the world have had the fortitude to say we are not okay with letting your neighbor die untreated. “No, don’t just go die.”
Then we have to get realistic enough to find a way to deal with that reality.
We’ve been trying to ignore reality – as if it will just go away – for decades.
A consensus can be had on some BASE level. Looking away doesn’t make it different. And in healthcare, repair ususally costs more than prevention.
And if we can get real and mature enough to say “the battle will be unending (fluid process) but in the end we’ll sleep better knowing we have some level of game plan for us all to reduce suffering”.
Which is really what it’s all about in the end isn’t it? Reducing suffering and premature death. Which is in essence a testiment to some level of progress from the stoneage for mankind. We can be better than that. Can we not move along in at least some basics of our human condition? Do we not have some level of universal human truths and standards? We do with things like the rule of law. Collective cimmoitments to each other. It’s not a novel concept; just one that takes mature honest and goals for our collective goup – aka: citizens of our nation.
Do we not have some level of universal human truths and standards? I think and hope we do.
bully bully
The best and brightest of the world didn’t immigrate to the US. We are their offspring.
I think the people who originally moved to what is now the US were either criminals, people running away from debt, or just liked adventure and travel.
Can you get a little more cynical perhaps?
+ war refugees (e.g., my dad’s side)
Waves of people left Europe after 2 major wars for jobs in the USA economy that benefited. Plus smaller wars too.
It’s an intentional part of the imperial operation: acquire not just Nazi rocket or Japanese biowarfare scientists but many more able-bodied people to spend their prime working years within the acquirer’s economy.
“Change is coming. The election results guarantee that.”
Really? I’m not sure you are paying attention. Trump was elected because he promised to do something about the corrupt Swamp. He made the Swamp more corrupt. Helping elect his opponents, all of whom like bigger (and therefore more corrupt) government.
It is reasonably well-documented that what the electorate wants is irrelevant more often than not.
When I finished residency in the mid 2000s most new ER docs would work 15 to 17 shifts a month as a full-time job. That is extremely rare nowadays as most new grads prefer to work 11 to 12 shifts even though their loan burden is likely quite a bit larger than mine was when I got out. I think many of them recognize how challenging the cognitive load of the work is and How the effects of the constant shift changes are a health hazard in their own right. This is true in other specialties as well and has implications for staffing predictions for lots of roles in medicine going forward.
As for Idaho, a few years ago I interviewed a candidate for my site who was leaving his EM job in Idaho. His wife was an obstetrician there and her entire group was disbanding / moving due to their strict abortion law. I can’t imagine working in a state where properly treating a miscarriage could put you in jail.
Three words: Demographic Death Spiral (DDS)
These three words will become common speak in about 3 years in 2030 when all 80 million screaming boomers hit 65 and start taxing the social security, medicare and other social programs to the limit. It won’t stop there, Gen X is right behind them.
The problems in this country continue to pile up a mile high so I look forward to see what the blue wave brings onto the shore in terms of solutions. I don’t actually expect any progress but we’ll see.
I found out a MAGA relative has some type of cancer that requires $6000/month in medication. He’s on medicare and the $6k comes out of pocket. The fam just smirked at his predicament about hating social programs and now having to shell out $72k/year for medicine. He has money but eventually he’ll go broke or he’ll die when the meds stop.
Two other boomers I know both need knee operations otherwise they can barely walk. Take those incidents and multiply x 80m and you may understand the 1500ft elder tsunami about to drown the country.
I have a neighbor with 3 joint replacements and assorted other ailments including an every other week visit from a nurse to maintain the pain pump that she has. No telling how much all this costs but I have a strong feeling that they exceed far and beyond what she ever paid into Medicare. Yet she will tell you that she “paid for her Medicare benefits and is due them.” To think all of that and then she also complains about her premiums going up 6 or so dollars a month…we should all have it so good!
Yeah, that’s the biggest crock boomers post comments on here. “I paid for it!”
Total nonsense. Your $30 medicare paycheck contribution doesn’t cover $500k+ of ongoing medical expenses. And I remind people they can easily look at their SSN contributions over at https://www.ssa.gov/myaccount/ and actually check their contribution and do the math. Never hear a peep from them again after that because they prefer to live in their own delusional boomer world.
The real scream will come in 2030 when there aren’t enough docs, nurses, or other healthcare workers for the volume. It’s not just a US problem, it’s a global one.
Most people either never heard or don’t remember the proverb: That which cannot be paid, won’t. – Herb Stein.
That is the direction entitlements are going. Rising costs, currency debasements, and a workforce not growing most places in the world.
Affording an entitlement system will be tested and it is not far in the future.
Where I live I’m not aware of Medicare supplement insurance going up $6 or so a month. Maybe a Part D drug plan could go up $6 per month.
The Part B premium is projected to increase by $6.60 to $209.50 per month (up from $202.90 in 2026.
I see. Your figures apply to the federal part B premium. They don’t include a Medicare supplement premium or premium increase for the supplement.
Wait till he passes and the government comes after his estate for medical bills.
I think that only applies when Medicaid is involved, not Medicare.
Thanks you are spot on.
We have to reframe and reassess our cost controls. Speaking of I’m typing this slower as my left hand is currently getting an IV. So i’ll address this later.Covered the subject for decades.
When you pump free money handouts into the system, cost controls go right out the window. This has been proven with all the free money handouts for Universities, Healthcare and the Military Industrial Complex. Anywhere government is handing out money results in inflation, fleecing, gouging and other problems.
We need a “free money handout” control more than anything else. Funny how X-rays cost 1/10th anywhere in Asia where there are little to no money hand outs as opposed to US rates.
There’s a lot to unpack here; but IMHO the worst economic cost driver is the indemnity health insurance that is the backbone of ONLY THE US SYSTEM.
Want to make more money? Just raise your rate. It’s premise of backstopping costs is the antithesis of cost control.
Until you say “we only have “X” to work with” you have NO cost control.
And BTW , why did Trump et al remove Medicaid’s right to negotiate prices? SO MUCH FOR USING BUYING POWER! BY PHARMAS BIGGEST CUSTOMER NO LESS.
NO NATION IN THE WORLD DOES NOT NEGOTIATE DRUG PRICES. FOR A REASON.
Only reason not to is political Kickback Bribes. Basic corruption 101.
bingo. winner of honesty. and insight. btw medicaide in NYS is wonderful. ask anyone here on it. i’m shocked as i was a huge skeptic when i moved back after being gone for 30 years to life.
Sounds like an experimental drug – and Medicare may not cover those. (As it shouldn’t).
Btw – not everyone gets arthritis. Some of us are blessed in that regard.
What could we have had instead of a disastrous failure in Iran? Do I get a single desirable thing from one Federal tax dollar? Is it asking too much that anything benefit the citizenry?
Idaho is well known for its potatoes.
You say “POtato” I say “aborTION.”
🙂
How about a public option? Fed gov uses its purchasing power to negotiate rates and sets up a federal health insurance company based on those rates. Caveats: FedGov cannot sell services below cost, and if you take one FedGov insured patient you have to take them all. Surely no one would be opposed to this, as we all know that the private sector would produce better care at lower cost.
Fed Gov health insurance as you describe is essentially just tax payer pays for everyones insurance.
If you think the government can negotiate the best rates you might want to think again. Lobbyists will just deliver a suitcase full of cash to whomever does the negotiating in order to get them to ‘buy at that price’. There’s no incentive for government employees to negotiate a great deal since it’s not their money.
If you don’t think that’s true, look at everything the governments (city, state, federal) already buy. They almost always pay the highest costs (union labor, buy from union shops/businesses etc).
Not sure I agree….Medicare pays providers just a fraction of what they ask for.
No, the correct place to look is Canada and every other first world country that has government sponsored or heavily regulated healthcare. On average the overall cost healthcare in these countries is 50% – 60% that of the US as a percentage of GDP, everyone is covered, and overall population health outcomes is far better than in the US.
In other countries there are no insurance bureaucracies trying to deny healthcare that rake off about 30% of insurance premiums, instead of actually paying for healthcare. Executive salaries and shareholder profits add further cost inefficiencies. The overall administrative cost for Medicare is less than 5%.
Government, single-payer healthcare around the world works. The US system is convoluted and insane by comparison.
Yes, it works.
Yeah but in the US if I want healthcare I get it today.
If you are in Canada and you want healthcare you get it whenever they get around to it. My family still lives there and they routinely wait months for things I can get tomorrow and the quality of what they do get leaves a lot to be desired.
Thanks but no thanks.
total horseshit. plenty of us have family there and live on the border. sell that crap to charlie kirk’s grifter widow. talk to any snow bird in AZ……..about reality.
FFS dude, many on southern border go to mexico for cheap dentist and medical care. on northern border we know you are full of shit. i lived on both borders for many years. you are full of bullshit.
If you don’t have healthcare, or cannot afford it, same thing, the wait is ENDless. In the US it is rationed health care like anywhere else, but with a proportion of the population excluded.
Not a human right and it isn’t free. Somebody somewhere is paying for it.
“There’s no incentive for government employees to negotiate a great deal since it’s not their money.”
Why do purchasers for Insurance companies have different results? It’s not their money either, it’s the company’s. Is it completely and utterly impossible for Congress to give FedGov purchasers the same incentives?
Because private insurance companies’ sole goal is to make as much money as possible, which means an endless focus on cutting expenses and increasing prices. The government mindset is to spend everything they have and then threaten to cut off benefits unless they are given more money.
It is a difference in culture. I would love to see plans made to improve this mindset. Neither corporations nor governments in America have healthy organizational cultures due to systemic issues.
And there is the problem. The magic word; lobbyists. Nothing gets fixed until lobbying is illegal. That will take one or two more elections like this past one. Schumer, McConnell, Pelosi, Jeffries, Cruz, and a host of others. All those corrupt sociopaths have to be voted out.